- What it treats
- Prostate cancer that has not spread beyond the prostate
- Incisions
- A few small cuts, 5 to 12 millimeters each
- Anesthesia
- General anesthesia
- Hospital stay
- Often one night
- Catheter
- Usually about one week
What is a robotic prostatectomy?
A radical prostatectomy removes the entire prostate gland, along with the seminal vesicles, two small glands attached to it. Depending on the extent and grade of the cancer, nearby lymph nodes may also be removed and checked for cancer (a pelvic lymph node dissection). Once the prostate is out, the bladder is reconnected to the urethra, the tube that carries urine out of the body.
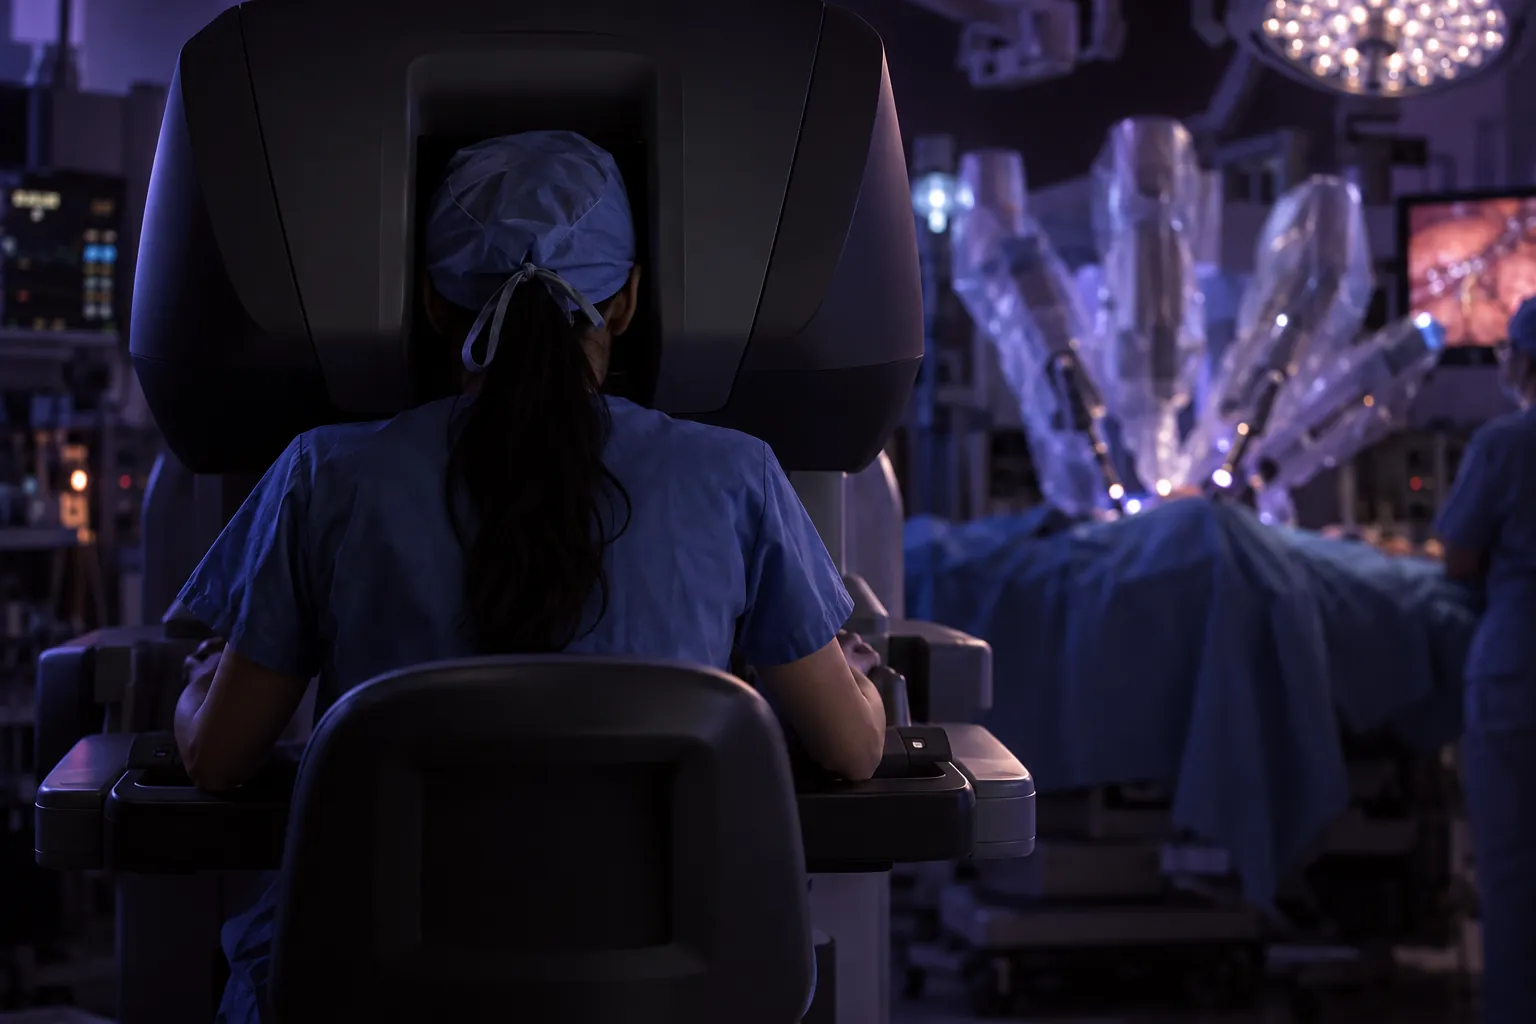
“Robotic-assisted” means Dr. Su performs the operation with the Intuitive da Vinci surgical system. The robot does not act on its own. She controls every movement from a console in the operating room.
How it is performed
In a multi-port robotic prostatectomy, Dr. Su places slim robotic instruments through several small incisions in the abdomen. Each is 5 to 12 millimeters across, about the diameter of a dime or smaller. One instrument carries a stereoscopic camera that gives her a magnified, three-dimensional view. The others hold specialized surgical tools that follow the movements of her hands precisely.
Robotic prostatectomy can also be done through a single small incision (single-port). Whether single-port or multi-port, the minimally invasive approach usually means smaller incisions, less pain, less blood loss, a lower chance of needing a blood transfusion and a shorter hospital stay than traditional open surgery.
Nerve sparing and bladder control
The nerves that control erections run in two thin bundles along the sides of the prostate. When the cancer allows, Dr. Su carefully separates these nerves from the prostate and leaves them in place. This is called a nerve-sparing robotic radical prostatectomy.
Whether nerve sparing is possible depends on how extensive the cancer is and where it sits in relation to the nerves. Dr. Su will discuss it with you before surgery, and the final decision is made during the operation, when she can see the tissue directly. The nerves may be spared on one side or both.
During surgery she also uses techniques that help protect the muscles that control urine, to support your recovery of bladder control. Her aim is to remove the prostate completely while doing as little harm as possible to the nerves and muscles around it.
Who is a good candidate?
Robotic prostatectomy treats clinically localized prostate cancer, meaning cancer that, based on your tests, appears to be contained within the prostate.
It may not be the best choice if you have:
- Cancer that has spread to other parts of the body (metastatic cancer). Men with known metastatic disease are not candidates.
- Cancer that has grown well beyond the prostate into nearby tissue
- Prostate cancer that has come back after earlier treatment (recurrent cancer), in some cases
- Extensive past abdominal surgery, or past radiation
- Serious heart or lung disease
- Severe obesity, or a tendency to bleed
- Advanced age, depending on your overall health
If surgery is not right for you, radiation therapy or focal therapy can serve as an alternative, or as an added treatment. A very large prostate can still be removed robotically, although the operation usually takes longer. Compare prostate cancer treatment options.
What recovery is like
In the hospital
Many patients stay one night. Dr. Su checks on you the next morning, and most people go home in the afternoon on the day after surgery. Getting up and walking soon after surgery helps your recovery.
The catheter
You go home with a urinary catheter, a soft tube that drains urine while the new connection between the bladder and urethra heals. It usually stays in for about one week and is then removed in the office.
The first weeks at home
Walking is encouraged. Avoid heavy lifting and strenuous exercise until Dr. Su tells you it is safe, usually several weeks. Your discharge instructions cover driving, bathing and pain control.
Bladder control
Some leaking of urine is common after the catheter comes out. For most men it improves steadily over weeks to months. Pelvic floor (Kegel) exercises help.
Erections
Erections often take longer to return, sometimes a year or more, even when the nerves are spared. Your age, your erections before surgery and whether the nerves were spared all play a part. Treatments can help while you recover.
Follow-up PSA tests
With the prostate removed, your PSA should drop to a very low level. Regular PSA tests afterward check that the cancer has not come back.
Why the robotic approach
Compared with traditional open surgery, robotic prostatectomy usually means a quicker recovery, less pain and smaller scars. The magnified 3D view and precise instruments help the surgeon work carefully around the nerves that affect erections and the muscles that affect continence.
Dr. Su completed her fellowship in robotic surgery and urologic oncology at the John Wayne Cancer Institute in Santa Monica, after a urology residency at Yale School of Medicine. Before you decide, she walks you through what to expect before, during and after surgery.
Questions patients ask
Is the robot doing the surgery?
No. Dr. Su performs the whole operation. She sits at a console in the operating room, and the system translates her hand movements into smaller, steadier movements of the instruments inside your body.
How long will I be in the hospital?
Many patients stay one night and go home the afternoon after surgery. The exact timing depends on how you are recovering.
Will I still be able to have an orgasm?
Yes, orgasm is still possible. It will be “dry,” though, because the prostate and seminal vesicles, which make most of the fluid in semen, are removed. This also means you cannot father a child naturally after surgery. If that matters to you, ask Dr. Su about banking sperm beforehand.
What if surgery isn’t right for me?
Radiation and focal therapy are alternatives for many men, and some low-risk cancers can be safely watched with active surveillance. Dr. Su will explain which options fit your cancer. See prostate cancer treatment options.
How do I prepare for surgery?
See your primary care provider for a pre-operative work-up within 30 days of your surgery and at least 2 days before it. Read the pre-operative instructions for which medicines to stop and what to bring.